Smilab Retention
Robotic Bending
A custom fixed retainer is bent robotically to match the patient’s digital model. It helps maintain the results of completed treatment without relying on patient compliance.
Why a clear retainer alone is not enough
Clear retainers are a valuable retention aid, but their success depends on patients wearing them consistently. Over time they are worn less often, and they can wear out, crack or get lost. In those gaps, teeth can drift back towards their original positions and the results of months of work are quietly lost. A fixed retainer is bonded to the inner surfaces of the teeth, so retention no longer depends on patients remembering to wear anything. The clear retainer is not dropped: the two are used together.
Why conventional fixed wires fall short
Twisted stainless steel wires and chain or braided wires have been used for decades, but the literature consistently reports three structural weaknesses:
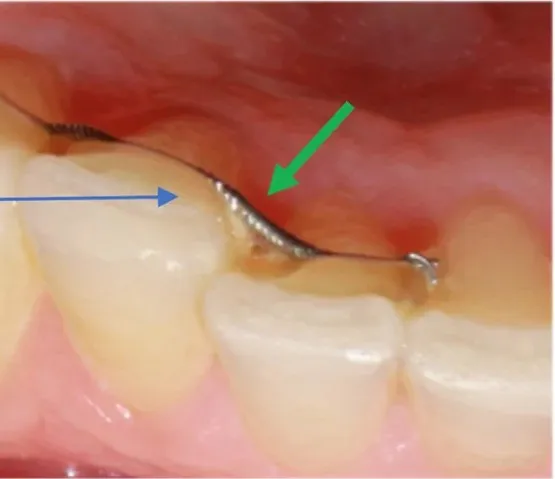
Metal fatigue and breakage
Repeated loading under chewing forces leads to fatigue and fracture over time. Published clinical series report breakage and detachment rates between 7.3% and 50%.²
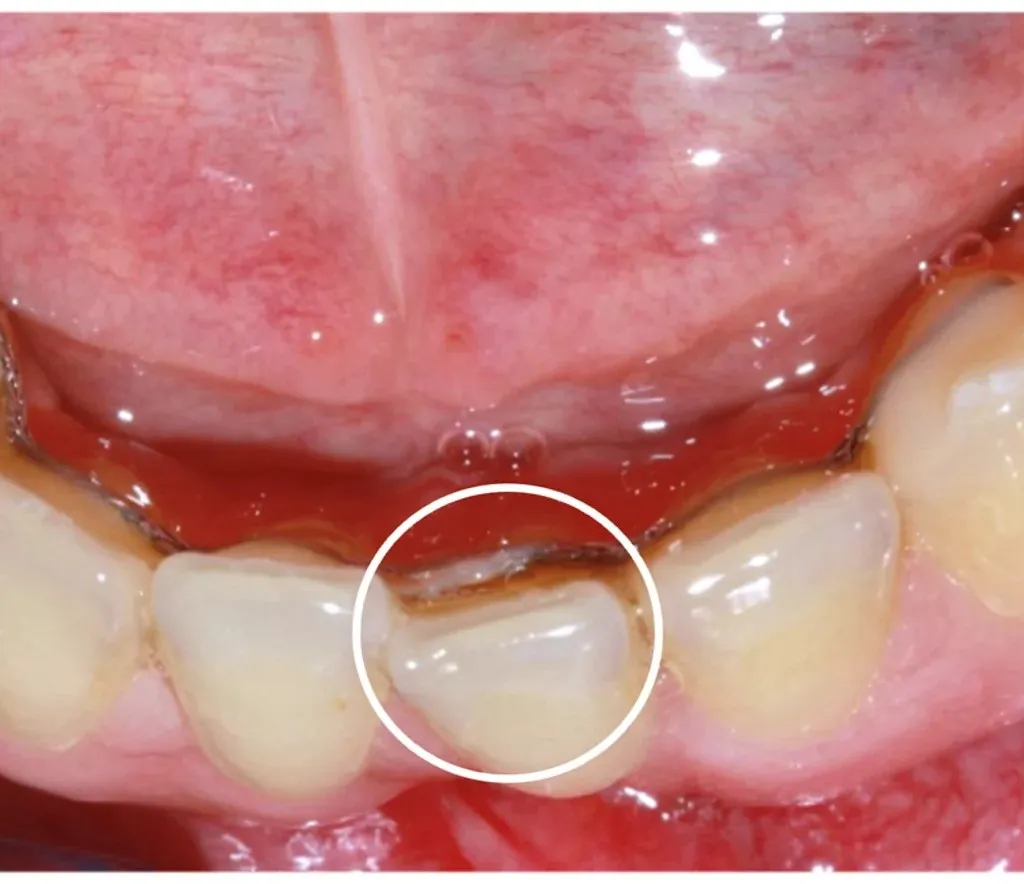
Debonding
The wire–composite bond is most at risk in the first 24 months. Bond failures are markedly more frequent in the first year.³
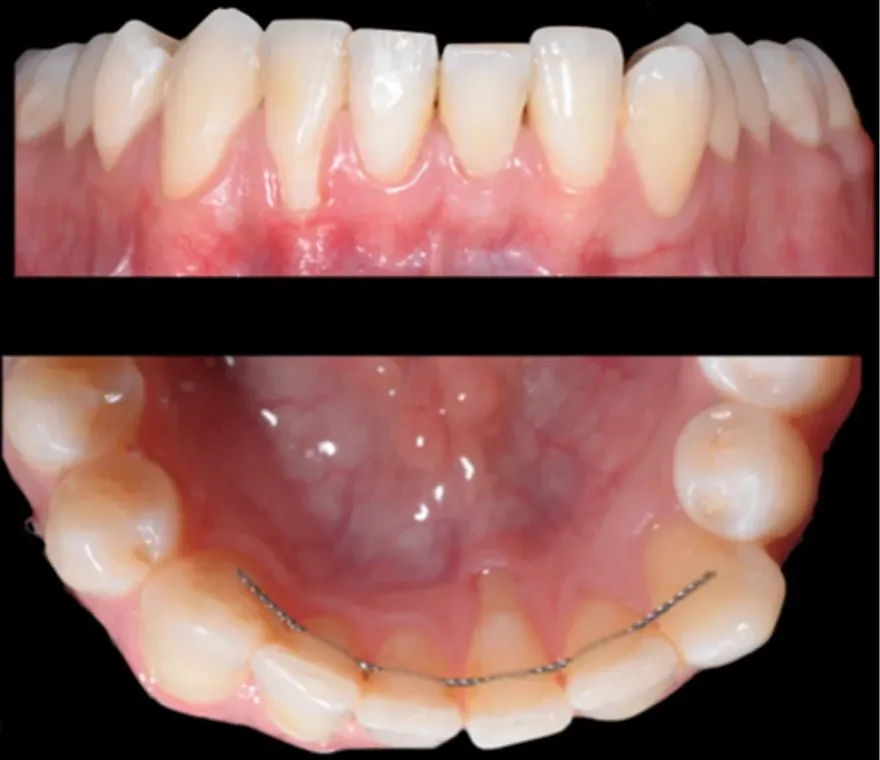
Unwanted tooth movement
Multistranded conventional retainers have been associated with inadvertent tooth movements (torque drift, x-effect) caused by wire activation. Chain-type wires adapted from jewellery were never designed for arch geometry.⁶
Photos: Dridi and Charavet, 2026⁷ · used under CC BY 4.0, cropped.
What sets Smilab Robotic Bending apart
A nickel-titanium (NiTi) fixed retainer, bent robotically to the patient’s digital model and engineered for permanent retention.
Superelastic NiTi
NiTi flexes far more than ordinary metals and returns to its shape. It is also used in medical devices such as stents and endodontic files. It is designed to reduce the fatigue-and-fracture cycle of hand-bent steel.⁴
Robotic bending precision
The wire is bent robotically to match the digital model of the patient’s tooth morphology. This gives the wire a passive, precise fit against the tooth surface, without the residual stresses caused by hand bending.
Advanced surface engineering
A dual-character surface treatment is applied to support composite adhesion to the wire.
Preserving physiological movement
A NiTi retainer allows natural (physiological) micromovement of the teeth. This flexibility has been reported as an advantage for patients who want to avoid long-term tooth loss due to root resorption.⁵
Clinical protocol
A fully digital workflow in four steps:
- 1
Digital impression
Impressions are taken only with an intraoral scanner, eliminating physical impression errors entirely. Before scanning, active elements such as power chains must be removed, and the final archwire should have been in place for at least 3 months.³
- 2
Robotic wire bending
A robotic system bends the wire to match the patient’s individual tooth morphology. No hand shaping is involved.
- 3
Passive fit and bonding
The wire fits passively against the tooth surface and is bonded using the recommended protocol (appropriate surface preparation + light-cured adhesive).
- 4
Combined retention with a clear retainer
For a more reliable result, combined use with a clear retainer is recommended for the first 2 years. For retainers fitted in the upper anterior region and in patients with a deep bite, daytime wear is advised in addition to night-time wear.
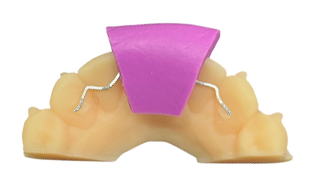
Case selection
The robot-bent retainer is not the first choice for every case. Let’s review the retention approach together in the following situations:
- Deep bite in the upper jaw (lower incisors contacting the retainer)
- Insufficient overjet (limited clearance between upper and lower incisors)
- Occlusal contact points in the anterior region
- Open bite
In these situations, our team assesses suitability using your digital impression and recommends an alternative retention approach if needed.
Already working with Smilab?
Doctor portalReferences
- Yu Y, Sun J, Lai W, Wu T, Koshy S, Shi Z. Interventions for managing relapse of the lower front teeth after orthodontic treatment. Cochrane Database Syst Rev 2013;9:CD008734. doi.org/10.1002/14651858.CD008734.pub2
- Jedliński M, Grocholewicz K, Mazur M, Janiszewska-Olszowska J. What causes failure of fixed orthodontic retention? – systematic review and meta-analysis of clinical studies. Head Face Med 2021;17:32. doi.org/10.1186/s13005-021-00281-3
- Egli F, Bovali E, Kiliaridis S, Cornelis MA. Indirect vs direct bonding of mandibular fixed retainers in orthodontic patients: comparison of retainer failures and posttreatment stability. Am J Orthod Dentofacial Orthop 2017;151:15-27. doi.org/10.1016/j.ajodo.2016.09.009
- Liou EJ, Chen LI, Huang CS. Nickel-titanium mandibular bonded lingual 3-3 retainer. Am J Orthod Dentofacial Orthop 2001;119:443-449. doi.org/10.1067/mod.2001.111397
- Roser CJ, Rues S, Erber R, Hodecker L, Lux CJ, Bauer CAJ. Tooth mobility restriction by multistranded and CAD/CAM retainers: an in vitro study. Eur J Orthod 2024;46(1):1-7. doi.org/10.1093/ejo/cjad076
- Zachrisson BU. The bonded lingual retainer and multiple spacing of anterior teeth. J Clin Orthod 1983;17:838-844.
- Dridi SM, Charavet C. Wire syndrome associated with multistrand orthodontic retainers: a proposed etiopathogenic concept. Dent J (Basel) 2026;14(9):540. doi.org/10.3390/dj14090540